Expanded clinical data flowing into Utah’s Clinical Health Information Exchange gives care teams statewide a more complete, timely view of the patients they share.
SALT LAKE CITY – When a patient leaves an Intermountain emergency department and shows up at a community clinic two days later, what travels with them matters. Their medications, their discharge summary, the results that came back after they left – that context is what separates a care team that’s prepared from one that’s starting from scratch.
Intermountain Health and Utah Health Information Network (UHIN) are announcing a significant expansion of the clinical data Intermountain contributes to Utah’s Clinical Health Information Exchange (CHIE). UHIN, Utah’s nonprofit health data steward, has operated the CHIE for more than 30 years with a single mission: better care and lower cost through interoperability that works for everyone. The expanded data sharing means more of that critical context is already waiting when the next care team needs it, across every setting where Intermountain patients receive care.
More complete data, from the moment care continues
For years, Intermountain has shared admission, discharge, and transfer (ADT) notifications for inpatient and emergency encounters through the CHIE. That foundation has grown substantially. Outpatient ADTs are now flowing, automated delivery of clinical documents and results has been activated, and the two organizations are actively working to add radiology reports, EKG results, pulmonary function test results, and clinical documentation covering all inpatient and outpatient discharges. Because Intermountain serves such a large share of Utah’s population, each new data type meaningfully increases what’s available to every provider across the state who shares patients with them.
What this means for care teams and their patients
For clinicians, the expanded data sharing reduces the blind spots that make care harder than it needs to be. Near real-time discharge notifications, paired with clinical summaries and results, support confident decisions at the point of care and timely post-discharge follow-up during the critical 72-hour window after a hospital stay. Better information also means fewer unnecessary repeat tests and a lower risk of the kind of errors that most often occur when records don’t follow patients from one setting to the next.
The people who stand to benefit most are those who navigate multiple care settings because of where they live, what their insurance covers, or the complexity of their health needs. These are often the patients least likely to have a single coordinated care team advocating for them, and the ones for whom gaps in the clinical record carry the greatest risk. A more complete shared record doesn’t just make care more efficient; for many patients it makes it meaningfully safer.
That’s especially true in emergency situations, when a patient may not be able to speak for themselves. Having prior clinical history available in those moments – current medications, known conditions, recent results – can make a critical difference in how quickly and accurately care is delivered.
Through UHIN’s participation in national networks including Patient Centered Data Home (PCDH) and eHealth Exchange, these benefits extend beyond Utah as well, with clinical information following patients as they move across organizations and state lines.
“What Intermountain has built here reflects something we don’t always get to celebrate in health IT: a health system that treats data sharing as a responsibility, not just a feature. The clinical record available to providers across Utah is meaningfully richer because of the work Intermountain and our teams have done together, and that ultimately shows up as better, more connected care for the patients we all serve.” – Navina Forsyth, Ph.D., M.P.A., Chief Data & Privacy Officer, UHIN
“As an emergency physician, I know exactly what it feels like to care for a patient whose story I can only see part of. Every missing medication, every unseen result, every prior visit we can’t find is a decision made with less than the full picture. Expanding what Intermountain contributes to the CHIE is one of the most tangible ways we can change that for the patients we share with providers across Utah. Our responsibility to the people we care for doesn’t stop at our doors, and neither should their record.” – Tamara Moores Todd, MD, Chief Health Informatics Officer, Intermountain Health
A shared resource, built by many
Intermountain’s expanded contribution builds on years of investment by the many Utah health systems, providers, and health plans that have shared data through the CHIE. The exchange works because organizations keep contributing to it, and what Intermountain has added strengthens something that belongs to the entire community. What makes this moment notable is not just the scope of what has been added, but the speed with which both teams made it happen – a reflection of what’s possible when organizations are genuinely aligned around a shared mission.
What’s next
Upcoming priorities include extending automated clinical document delivery to cover all inpatient and outpatient discharges, along with adding radiology reports, EKG results, and pulmonary function test results to the data flowing through the CHIE. Each addition moves Utah closer to the kind of continuous, portable clinical record that makes genuinely coordinated care possible across every setting where patients receive it.
About UHIN
UHIN is Utah’s nonprofit, neutral data trustee, connecting providers, payers, and public health through trusted, interoperable infrastructure that improves care across the state and beyond. As both Utah’s state-designated health information exchange (HIE) and a full-service clearinghouse, UHIN sits at the intersection of clinical and administrative data. For more than 30 years, this community-anchored, mission-driven model has reduced administrative burden, improved care coordination, and delivered measurable value in cost, quality, and outcomes. Rooted in Utah. Connected nationally. Committed to turning better data interactions into better care.
About Intermountain Health
Intermountain Health is a nonprofit system of 34 hospitals and ~400 clinics across six western states, employing 4,600+ providers and serving 1M+ Select Health members. Focused on community health and evidence-based care, the system is a leader in high-quality, sustainable healthcare.
Media Contacts
UHIN: Desiree Jenkinson, Head of Marketing, djenkinson@uhin.org, 877-693-3071
Intermountain Health: Lance Madigan, Media Relations Manager, Lance.Madigan@imail.org, 801-442-3217
Prior authorization has frustrated providers, payers, and patients for decades. Phone calls to utilization review departments. Faxed documentation. Multi-day waits while care is on hold. The administrative cost alone runs into the hundreds of billions annually across the healthcare system, and the human cost is harder to quantify but just as real.
Over the last two years, federal regulators have moved decisively to change that. And the standards bodies that underpin how healthcare data actually moves have been working even longer to build the infrastructure those regulations require.
At UHIN, we haven’t been watching this from the outside. We’ve been inside the rooms where implementation gets figured out, and we’ve been there by design.
Here’s what’s shifting, why it matters to you regardless of your role, and what it means to have a partner who was already invested in this work before it became mandatory.
What’s Changing, Rule by Rule
CMS-0057-F: Interoperability and Prior Authorization
Finalized in January 2024, CMS-0057-F is the most significant overhaul of prior authorization workflows in HIPAA history. It requires Medicare Advantage, Medicaid, CHIP, and qualified health plans on the federal exchanges to implement four FHIR-based APIs: Patient Access, Provider Access, Payer-to-Payer, and Prior Authorization. Full API compliance is due January 1, 2027.
Operational requirements came first. As of January 1, 2026, payers are required to issue standard prior authorization decisions within seven calendar days and expedited decisions within 72 hours.¹ Payers also began publicly reporting prior authorization metrics (approval and denial rates, average decision times, appeals outcomes) starting March 31, 2026, covering calendar year 2025.²
On the technical side, the rule centers on HL7 FHIR R4 infrastructure and SMART on FHIR for authentication. The Da Vinci Project’s implementation guides define the workflows those APIs are expected to support. The Coverage Requirements Discovery (CRD), Documentation Templates and Rules (DTR), and Prior Authorization Support (PAS) guides collectively describe how a provider system can determine whether authorization is needed, surface documentation requirements, and submit a request without leaving the clinical workflow.³ These are the standards the industry is actively working to implement, and organizations are at different stages of readiness across all three.
There’s also a meaningful shift in how FHIR and X12 coexist. CMS issued enforcement discretion allowing payers to implement a FHIR-only Prior Authorization API without being required to also use the X12 278 transaction.⁴ For the first time in HIPAA history, FHIR can function as a standalone path rather than a complement to EDI. The 278 remains valid, and many real-world implementations will use a hybrid model where FHIR faces the provider side and X12 handles the back-end translation.
CMS-0053-F: Claims Attachments
Finalized March 24, 2026, CMS-0053-F establishes the first-ever HIPAA-adopted standards for healthcare claims attachments. It goes into effect May 26, 2026, with a compliance deadline of May 26, 2028.⁵
For decades, claims-related clinical documentation (medical records, imaging, lab results, clinical notes, telemedicine visit documentation) has moved via fax, mail, and payer-specific portals. This rule requires payers to support standardized electronic attachment transactions, though payers may continue accepting other forms of submission if they choose to. In practice, many payers today already discourage or decline non-electronic methods, and this rule formalizes the electronic standard they must support. Specifically, it adopts Version 6020 of the X12N 275 for provider-to-payer transmission of supporting documentation and the X12N 277 for payer requests to providers, along with HL7’s Consolidated Clinical Document Architecture (C-CDA) for structuring the clinical content inside those transactions.⁶
One thing to note: CMS did not finalize prior authorization attachment standards in this rule. That question is still open, with HHS continuing to evaluate how FHIR-based workflows, X12, and C-CDA should align. A CMS listening session in December 2025 addressed replacing the X12 278 with HL7 FHIR under the exception process.⁷ Stakeholder input is still actively shaping what comes next.
X12 Version 8060: The Next HIPAA Transaction Standard
Version 5010 has been the HIPAA-mandated X12 standard for administrative transactions since 2012. X12 published its 008060 EDI Standard in January 2025 and completed the full set of 008060 implementation guides for all HIPAA-mandated transactions in September 2025. The updated guides cover claims (837), eligibility (270/271), claim status (276/277), remittance (835), enrollment (834), and premium payment (820).⁸
X12 has formally recommended to the National Committee on Vital and Health Statistics (NCVHS) that 008060, along with its XML representation, be adopted.⁹ Version 5010 remains the current mandated standard while federal rulemaking proceeds. WEDI, as an official advisor to HHS, has been conducting its own Federal Policy Consultation process to gather industry input on the impacts, costs, and timing of the 8060 transition, with findings submitted to HHS.¹⁰ HHS convened an additional listening session with the Designated Standards Maintenance Organizations (DSMOs) and WEDI on July 1, 2026, specifically to gather perspectives on the proposed 5010-to-8060 transition; that feedback will inform future HIPAA Administrative Simplification rulemaking.¹¹
X12 has also launched a 2026 education series to help implementers understand what’s changing and prepare their systems before any mandate takes effect.¹²
For organizations managing EDI workflows, this transition will eventually touch every major transaction type you process. Now is a reasonable time to start asking questions and building familiarity with what’s different in 8060.
Why Clearinghouses Are Central to Making This Work
It’s tempting to think of prior authorization modernization as a simple point-to-point story: EHR sends a FHIR bundle, payer system responds, authorization decision arrives in minutes. That’s the goal. The path there is more layered.
Most providers don’t have direct FHIR connections to most payers. Many payer systems aren’t yet equipped to receive FHIR-based prior authorization requests natively across their full network. The translation work, routing between networks and managing acknowledgments, is precisely what clearinghouses are built to handle.
The HL7 Da Vinci Prior Authorization Support implementation guide makes this explicit: clearinghouses are one of the designated intermediary roles responsible for ensuring HIPAA transaction compliance while FHIR operates on the provider-facing side.¹³ The X12 handling happens in what the Da Vinci guide calls a “black box,” a service that the submitting system doesn’t need visibility into. That service is often a clearinghouse.
This isn’t a workaround. It’s the intended architecture for how hybrid environments function during the transition from legacy EDI to FHIR-native exchange. Getting the translation layer right, and getting it right across networks rather than just within individual point-to-point connections, is where the real implementation work lives.
Where UHIN Fits In
UHIN isn’t simply tracking these changes and updating our systems to match. We’re actively involved in building the frameworks the industry will follow.
Da Vinci Trebuchet: Clearinghouse-to-Clearinghouse Prior Authorization Pilot
In early 2025, UHIN was selected as a participant in the Da Vinci Trebuchet Clearinghouse-to-Clearinghouse (CH-to-CH) Prior Authorization Pilot, launched by the Cooperative Exchange in collaboration with the HL7 Da Vinci Project. The cohort includes eleven clearinghouses, including Waystar, Optum, Availity, and Veradigm, working to test whether FHIR-based prior authorization transactions can actually be operationalized across clearinghouse networks rather than just within individual point-to-point connections.¹⁴
The pilot is validating hybrid X12 and FHIR translation workflows that reflect how the industry actually operates today. The outcomes include a functional prototype, a clearinghouse implementation playbook, and concrete recommendations for improving the underlying standards including Da Vinci, FAST Implementation Guides, and X12. When those recommendations get made, UHIN will have helped shape them.
Utah Statewide FHIR Interoperability Pilot
UHIN is also a central participant in Utah’s statewide FHIR interoperability effort through the One Utah Health Collaborative, with clinical data exchange and prior authorization as the two primary use cases. UHIN has contributed patient attribution data, connectivity infrastructure, and coordination across payers, providers, and public health stakeholders working toward a shared FHIR-based ecosystem across the state.¹⁵ UHIN’s CTO participated in Civitas’s FHIR Deep Dive Series in early 2025 to share progress on that work with a national audience.
The CHIE on FHIR, Already Live
In late 2024, UHIN launched a modernized Clinical Health Information Exchange (CHIE) portal built on HL7 FHIR, supporting data sharing across 33 of 36 short-term acute care hospitals in Utah. This wasn’t a pilot or a roadmap commitment. It’s in production.¹⁶
Active Standards Participation
UHIN is a recognized Standards Development Organization with ongoing participation in national electronic transaction committees. We attend X12 standing meetings, engage with HL7 workgroups, and track NCVHS recommendations and comment cycles. When CMS convened its December 2025 listening session on the question of replacing the X12 278 with HL7 FHIR, the voices of organizations like ours were part of what informed that conversation.¹⁷
What This Means for Your Organization
For EDI and revenue cycle teams: The 5010-to-8060 transition is not a mandated deadline yet, but the implementation guides are published, X12 is running education sessions now, and rulemaking is in motion. Getting familiar with what’s changing before the deadline appears is time well spent. Start by asking what’s different in 8060 for the specific transaction types you handle most.
For payers: The January 2027 FHIR API compliance deadline is closer than it looks once you account for integration timelines, testing cycles, and the organizational lift of standing up four APIs while also meeting the operational requirements that went live in January 2026. The clearinghouse layer handles the hybrid translation and provider-side connectivity that makes network-wide adoption feasible rather than theoretical.
For providers and revenue cycle leaders: CMS-0053-F requires payers to support standardized electronic claims attachment transactions by May 2028. Many are already moving in that direction now. Understanding what the X12N 275 and 277 transactions require, and how C-CDA structures the clinical content within them, will help you prepare for what your trading partners will eventually expect.
For compliance and technology leadership: The convergence of CMS-0057-F, CMS-0053-F, and the 8060 transition represents the most significant wave of HIPAA administrative simplification updates in over a decade. These rules interact with each other. The FHIR enforcement discretion for the 278 directly shapes how prior authorization attachment standards will eventually be decided, which CMS explicitly left unresolved pending further industry evaluation. Understanding how the pieces connect is as important as understanding each piece on its own.
Already Here Before the Mandate
UHIN has been at this for more than thirty years. We process hundreds of millions of transactions a year. We operate the nation’s only nonprofit clearinghouse network. We run Utah’s state-designated Health Information Exchange. And we sit at the table where standards get written, not just where they get implemented.
The regulatory changes coming into effect over the next two years reflect years of industry collaboration, standards development work, and pilot programs that UHIN has actively contributed to. We aren’t scrambling to catch up with what compliance requires. We’re already working on what comes after that.
If you want to talk through where your organization stands on any of this, we’re here for that conversation.
References
CMS. CMS Interoperability and Prior Authorization Final Rule (CMS-0057-F) Fact Sheet. January 2024. cms.gov
CMS. CMS Interoperability and Prior Authorization Final Rule (CMS-0057-F). January 17, 2024. cms.gov
HL7 Da Vinci Project. Da Vinci Prior Authorization Support (PAS) FHIR IG v2.1.0. hl7.org
CMS National Standards Group. HIPAA Transaction Enforcement Discretion. February 28, 2024. cms.gov
AAPC. CMS Final Rule Standardizes Electronic Healthcare Data Exchange. March 31, 2026. aapc.com
CMS. Administrative Simplification; Adoption of Standards for Health Care Claims Attachments Transactions and Electronic Signatures Final Rule (CMS-0053-F) Fact Sheet. March 2026. cms.gov
CMS. Events and Latest News: Administrative Simplification. December 2025 Listening Session. cms.gov
X12. X12 Publishes 008060 Versions of All HIPAA-Mandated Implementation Guides. September 2025. x12.org
X12. X12 HIPAA Recommendation Letter. December 2025. x12.org
WEDI. WEDI’s Federal Policy Consultation Process and X12 Version 008060. March 2026. wedi.org
CMS. Events and Latest News: Administrative Simplification. July 1, 2026 Listening Session. cms.gov
X12. Announcing the Kick-off of X12’s 008060 Education/Information Series. March 2026. x12.org
HL7 Da Vinci Project. Da Vinci Prior Authorization Support (PAS) FHIR IG: Use Cases and Overview. hl7.org
UHIN. Newsletter: January 2025 Issue. February 2025. uhin.org
One Utah Health Collaborative. Advancing Interoperability in Healthcare: Utah’s Collaborative Approach. 2025. uthealthcollaborative.org
UHIN. 2024 Year-End Recap. 2025. uhin.org
CMS. Events and Latest News: Administrative Simplification. December 2025 Listening Session. cms.gov
Healthcare works best when information moves as seamlessly as care itself.
With the right data and context, decisions are made faster and with greater confidence. When organizations share information responsibly, operations become more efficient. When communities invest in shared infrastructure, everyone benefits.
That’s the promise of healthcare interoperability. Realizing this promise of a fully connected network requires more than just agreeing with the philosophy – it requires organizations to take specific, concrete actions to participate.
A Shared Vision for Better Care
Utah’s healthcare community has long understood something essential: no single organization delivers care alone.
Patients move across settings. Doctors collaborate across systems. Health plans support care across populations. Government partners steward statewide health priorities. Outcomes depend on timely, accurate information wherever care happens or when decisions about patient care are made.
Interoperability makes this possible not by replacing existing systems, but by connecting them. It creates a foundation where information flows securely, consistently, while supporting a myriad of use cases.
This foundation is what UHIN provides today.
Infrastructure That Grows Stronger Together
UHIN operates Utah’s health information highway, the Clinical Health Information Exchange, or, the CHIE.
Utah’s shared infrastructure gives healthcare organizations secure access to comprehensive patient records across organizational boundaries.
Utah’s health information highway is designed to support all organizations who assist in the care, treatment, and health of Utah’s patients, including different providers across different systems to work as a single team to support the care journey of their shared patients. Effective information exchange requires infrastructure that adapts to how different stakeholders actually work: providers making real-time clinical decisions, health plans coordinating care across populations, and public health agencies tracking community-level outcomes.
The CHIE is a Shared Network
Managing dozens of point-to-point integrations is expensive, creates operational drag, and limits visibility across the care continuum. A shared network offers a different model: one connection that enables information to move across care settings, organizations, and systems.
Utilizing the CHIE, clinicians gain access to timely patient context, health plans can better support coordinated care and quality efforts, and public partners gain clearer insight into healthcare activity across the state. This all makes coordination easier to manage at every handoff – Health Plan to Provider, Health Plan to Health Plan, and Health Plans and Providers to Public Health.
Common Governance Instead of Fragmented Agreements
Trust is foundational to healthcare information exchange. The CHIE establishes a consistent, locally governed framework that supports responsible data sharing. Rather than navigating a patchwork of agreements, policies, and exceptions, UHIN welcomes organizations to participate within clear standards that promote accountability, transparency, and confidence across the ecosystem.
You save costs that are related to manually responding to data access and data sharing requests, and eliminate the time and expense spent on multiple legal and data transfer agreements – the CHIE already has them.
Common Stewardship Instead of Vendor Dependency
Infrastructure should serve the community it supports, not shift direction with market cycles or commercial priorities. UHIN operates as a neutral, non-profit utility, ensuring that Utah’s healthcare connectivity remains guided by community needs. Providers, payers, and public stakeholders collectively shape how the network evolves, supporting long-term sustainability and adaptability.
Together, these principles transform interoperability from a technical capability into a shared asset that grows stronger as participation increases.
Help Shape the Future
How do you know if your organization is helping build the healthcare network we all want to improve health outcomes and reduce costs?
To start, you should ask yourself and members of your organization these five questions:
1. Are you realizing the full value of interoperability?
Compare the membership fee to what you would have to pay to establish separate legal agreements and interfaces with each agency that UHIN connects with or manually respond to and submit records requests.
2. Are you using shared data to improve patient outcomes?
Connecting the pipe is the first step to make a real clinical difference. The next step is integrating CHIE data into workflows ensures providers actively use shared context to make smarter, safer decisions.
For example, Granger Medical Clinic used CHIE ADT alerts to grow patient identification from one per week to 750 per month, cutting readmission rates by 61%.
Tanner Clinic and Connect TCM brought their average readmission rate down to 4% — far below Utah’s 13.9% and the national average of 14.6%.
3. Are you actively sharing?
Passive consumption helps one organization; active sharing strengthens care coordination, improves outcomes, and elevates the entire system. Sending ADT feeds, lab results, and patient records in real time ensures everyone has the information they need, when they need it. Sharing a comprehensive, high-quality record empowers better clinical decisions and reduces gaps in care.
4. How is this community asset funded?
Your financial support through donation or membership sustains the maintenance, innovation, and long-term growth of the data sharing infrastructure that serves us all. UHIN also applies for grants to support the important work the CHIE provides to our community.
5. Do you want to be more engaged, but don’t know how?
For Current CHIE Users: Assess if your organization is helping shape the future of interoperability by asking yourself the questions above. Then, log in at www.uhin.org today to experience the modernized CHIE Platform firsthand. If you need a hand with your account, please contact customer support.
For Former CHIE users or New Organizations: Visit the CHIE Platform page to get the information you need to get started. If you’re ready to connect to the CHIE, you can get started here.
The value to the community of the exchange is realized when every participant holds themselves accountable to these standards. Organizations that ensure their data is timely, complete, and accurate (and who financially support the infrastructure) are the ones shaping the future of Utah healthcare interoperability.
To join this vital cause, organizations must implement the following concrete steps:
1. Move from consumption to contribution: Care does not begin or end within organizational boundaries. The network is strongest when you contribute the timely, complete, and accurate data that the next provider in the chain needs. Organizations must connect to the CHIE and actively share data, specifically by setting up ADT feeds, patient records, and lab results.
2. Align your care teams: Healthcare is a team effort. Shared infrastructure enables collaboration, but only if your internal workflows support it. Ensure your teams are utilizing the data available in the CHIE to gain a complete picture of patient history.
3. Tackle community challenges together: Leaders who build community infrastructure recognize that progress accelerates when stakeholders work from a shared foundation. Participation strengthens not only individual organizations but the resilience and responsiveness of Utah’s healthcare system as a whole.
4. Commit to the infrastructure: If you are relying on the network but not supporting it, becoming a paying member ensures this resource remains available and robust for the long term.
These leadership choices shape how care is delivered today and how it will evolve tomorrow.
A New Chapter for the CHIE
For organizations that have connected to the CHIE in the past, now is the time to take a fresh look.
UHIN’s platform has been modernized and enhanced to better support today’s care delivery needs. The CHIE is more capable, FHIR-aligned, and better positioned to scale as the healthcare community grows. The CHIE is working to assess statewide membership and data quality to improve the data available to the community. Providers, health plans, and public partners engaging with the CHIE today are experiencing a network designed for the future of healthcare in Utah.
If you’ve tried it before, you may be surprised by how much better it is now.
Across Utah, organizations are already using shared infrastructure to support care delivery, coordination, and statewide initiatives.
New CHIE Dashboard
Moving Forward, Together
Behind every data feed, every alert, and every shared record is a patient whose care depends on a connected, informed care team. Utah’s information highway is in place. Its power is unlocked when every organization on the care continuum commits to using it fully. That’s how interoperability becomes more than a technical achievement — it becomes a promise kept to the people we serve.
Here is how to get involved:
For Current CHIE Users: Assess if your organization is helping shape the future of interoperability by asking yourself the questions above. Then, log in at www.uhin.org today to experience the modernized CHIE Platform firsthand. If you need a hand with your account, please contact customer support.
For Former CHIE users or New Organizations: Visit the CHIE Platform page to get the information you need to get started. If you’re ready to connect to the CHIE, you can get started here.
UHIN has played a pivotal role in a recent Centers for Disease Control and Prevention (CDC) project aiming to track the burden, distribution, and impact of Post-COVID conditions (PCC) in Utah. This initiative, detailed in a study published in BMC Public Health, leverages electronic health records (EHRs) and data from The CHIE (Clinical Health Information Exchange) to identify and analyze cases of PCC, commonly known as long COVID. Researchers aim to understand the prevalence, demographic distribution, and healthcare utilization patterns associated with PCC.
The study provides insights into the long-term effects of COVID-19 and highlights the importance of continuous surveillance to address the ongoing health challenges posed by the pandemic.
UHIN, as the only HIE in Utah, was an important contributor to this research. Since 1993, we have been committed to reducing healthcare costs and improving the quality of care through secure electronic data interchange. Our extensive network connects healthcare insurers, physicians, hospitals, laboratories, local health departments, and state agencies, enabling seamless data sharing across the state’s healthcare ecosystem.
In this project, UHIN provided a limited dataset including PCC cases and patient trajectories over time. By providing a limited dataset, UHIN was able to support the project, as allowed under HIPAA, while maintaining patient privacy and data integrity.
Collaborative Approach
A collaborative approach fostered partnerships among various healthcare entities, facilitating the aggregation of diverse data sets. Partners in this work are BeyondHIE, Indiana University, Boise State University, the Bronx Regional Health Information Organization (Bronx RHIO) and Comagine Health (our affiliate partner). This inclusivity enabled a more comprehensive understanding of PCC, as data from different sources provided a holistic view of patient experiences and outcomes. UHIN’s commitment to interoperability and data standardization was key to harmonizing information from multiple providers, ensuring consistency and reliability in the study’s findings.
In Conclusion
The success of this project underscores UHIN’s vital role in national health initiatives. By serving as a central hub for health information exchange, UHIN not only supports clinical care but also empowers research efforts that address pressing health concerns. Our infrastructure and expertise in data management are assets in the ongoing battle against COVID-19 and its long-term effects.
Our involvement in this PCC surveillance project adheres to our mission to enhance healthcare through innovation, collaboration, and inclusiveness. By providing the tools and frameworks necessary for comprehensive data analysis, we are proud to continue to contribute significantly to public health research and the improvement of patient care.
There is a national trend of Health Information Exchanges (HIEs) evolving into Health Data Utilities (HDUs). What is a Health Data Utility? The Consortium for State and Regional Interoperability defines a HDU as “a locally governed, public-private resource providing a source of truth for robust clinical and non-clinical data” to benefit state and other members of the healthcare ecosystem by providing data.
Much of the conceptualization of HDUs was done by Civitas Networks for Health, The Maryland Health Care Commission & CRISP, and the Consortium for State and Regional Interoperability. The HDU is the next phase for HIEs, recognizing that the data in an HIE is a valuable resource that can be utilized beyond just single patient lookup. It can be utilized for quality improvement, population health, research, and combined with other datasets for advanced analysis.
Data is the Lifeblood of an Organization
There is a saying that data is the lifeblood of an organization. Data is critical to identify areas and populations of need, understand and describe current status, evaluate interventions, improve efficiency, inform decisions, discover and adapt to changing conditions, and drive innovation. The COVID pandemic highlighted both the need for data and to identify gaps in data accessibility. The federal government has been working for the past two decades to improve the collection and availability of data to improve health care through initiatives such as the Health Information Technology for Economic and Clinical Health Act (HITECH), the formation of the Office of the National Coordinator (ONC), the 21st Century Cures Act and its Information Blocking provisions, and the Trusted Exchange Framework and Common Agreement (TEFCA) for national health information exchange. HDUs provide the infrastructure for data accessibility.
What HDUs Can Do
Data is critical to identify areas and populations of need, understand and describe current status, evaluate interventions, improve efficiency, inform decisions, discover and adapt to changing conditions, and drive innovation. The COVID pandemic highlighted both the need for data and to identify gaps in data accessibility. The federal government has been working for the past two decades to improve the collection and availability of data to improve health care through initiatives such as the Health Information Technology for Economic and Clinical Health Act (HITECH), the formation of the Office of the National Coordinator (ONC), the 21st Century Cures Act and its Information Blocking provisions, and the Trusted Exchange Framework and Common Agreement (TEFCA) for national health information exchange. HDUs provide the infrastructure for data accessibility.
Necessary Conditions
Necessary conditions for a HDU are considered to be a shared vision, political will/state policy, broad stakeholder participation, multi stakeholder governance, a legal framework, mature use cases, data privacy and security, and secured funding. The American Language Exchange Council has developed model language for a Statewide Health Data Utility Act. They believe that a “state health data utility can help achieve better patient outcomes, and improve overall health and wellbeing of the people of the state. It can also reduce the cost of healthcare services by creating a more seamless, transparent, and modernized approach to sharing health information. The health data utility will comply with all federal and state privacy laws and allow for an opt-out for patients who choose not to share their data.”
In Conclusion
UHIN established the Utah Clinical Health Information Exchange in 2007 to bring together a patient-centric, longitudinal record amongst disparate healthcare systems and organizations. We strive to make data accessible for better costs and better care. Evolving into an HDU, while also balancing patient privacy needs, is the next step.
CIVITAS Call for Public Comment: HDU Framework Supplement Version 1
Civitas Networks for Health invites public comment on the draft HDU Framework Supplement Version 1, which outlines critical updates to the existing Health Data Utility Framework. This supplement highlights actionable strategies for advancing health data governance, interoperability, and equity across states and regions.
It’s been a busy and rewarding month! We connected with our CHIE customers, sharing valuable insights and updates on the new portal experience. We proudly took part in recognizing the Utah Model of Care as a member of the One Utah Health Collaborative’s Stakeholder Community Board. On top of that, we posted the top five takeaways from our virtual payer panel, attended the Texas Association of Health Plans conference, and shared that Brian Chin will assume the role of Chief Product Officer at Comagine Health, in addition to his position as CEO of UHIN.
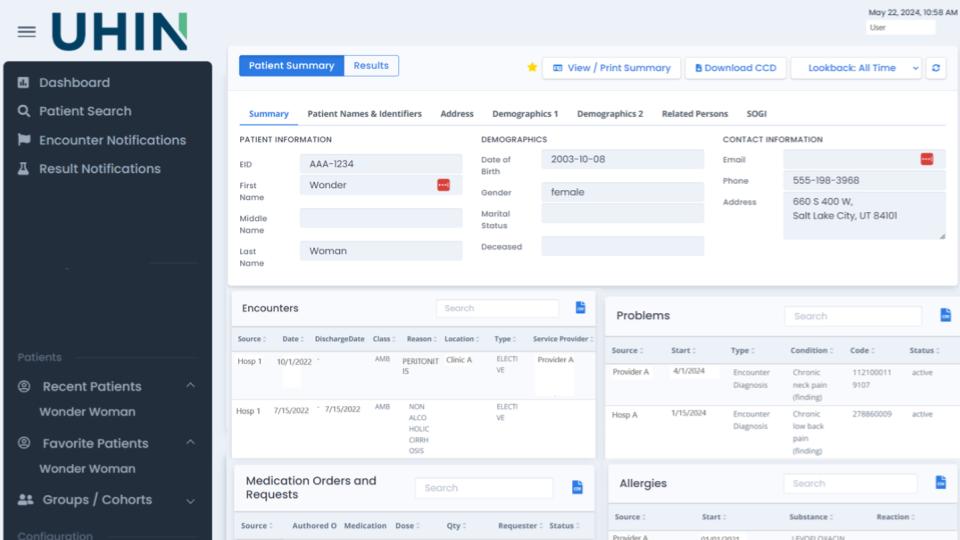
The new CHIE portal is live, offering a more modern user interface to access your patients’ longitudinal health records. We’ve created several methods to set you up for success.
CHIE portal users can watch engaging videos that walk you through the new portal features and powerful new tools, and how to log-in through MYUHIN.
Additionally, users can dive deeper into our comprehensive user guide which breaks down every feature step-by-step.
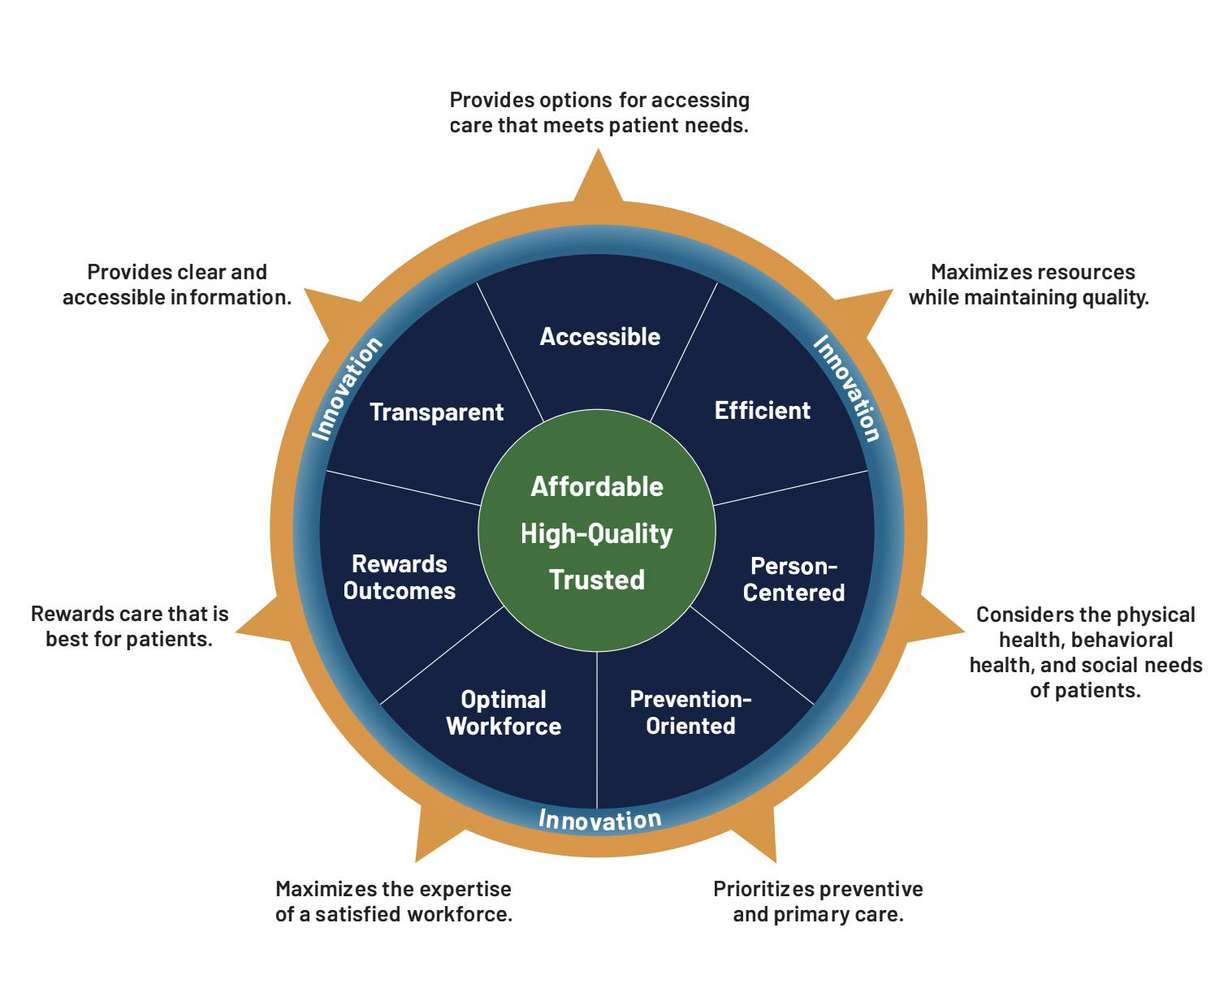
Prioritizing a System that is “Affordable, High-Quality and Built on Trust”
The One Utah Health Collaborative announced the adoption of the Utah Model of Care at the Capitol in late October. The model, developed through statewide collaboration, represents a significant step toward creating a healthcare system that is affordable, high-quality, and trusted for all Utahns. UHIN is proud to be part of the Stakeholder Community Board working with the One Utah Health Collaborative on the Utah Model of Care!
Top Questions and Answers from the Virtual Payer Panel
Dive into five of the top questions and insights shared during the webinar with Lori Weber (Noridian Healthcare Solutions) and Melissa Shoemaker (Select Health), offering clarity on telehealth billing, claims processing, EDI recertification preparation and other essential topics.
We attended the Texas Covered Health Care Conference + Expo Event in Austin, TX from November 4-6.
UHIN will be closed for the Thanksgiving holiday on Thursday, November 28th and Friday, November 29th. We’re thankful for our customers, colleagues, community and partners!
Please note: UHIN Customer Support Holiday Schedule
The UHIN Customer Support call center will be closed on Thursday, November 28th and Friday, November 29th. All regular support issues will be addressed on Monday, December 2nd.
Our on-call team will actively monitor the system to ensure connectivity remains stable. If you have an issue, please contact us through the standard support channels by emailing customersupport@uhin.org. These will be addressed in accordance with our off-hours support policies.
Trainings and Webinars
Watch the CHIE Portal Overview Video
The new platform offers a more modern user interface to access your patients’ longitudinal health records. Learn more about the updated experience in our demo video, including the new dashboard, cards, patient summary, customer support, and future enhancements.
Brian Chin tapped as Comagine Health’s Chief Product Officer
Comagine Health recently announced that Brian Chin will take on the role of their Chief Product Officer, while continuing to serve as CEO of UHIN. In his expanded role, Mr. Chin will lead the development and execution of Comagine Health’s product and technology roadmap, driving their commitment to providing high-quality solutions that meet the changing needs of the clients and the communities they support.
Health Information Exchanges (HIEs) have worked on interoperability for over a decade. Interoperability is crucial for improving patient care, reducing medical errors, and reducing avoidable procedures and unnecessary rework. The Information Blocking Rule (IBR), a part of the 21st Century Cures Act, aims to prevent healthcare providers and other entities from hindering interoperability or the exchange of electronic health information (EHI). This rule prohibits actions that intentionally restrict or interfere with the access, exchange, or use of electronic health information, promoting a more interconnected healthcare ecosystem. By fostering interoperability, IBR empowers patients and healthcare providers to access and share health information efficiently, leading to better-coordinated care and improved health outcomes.
This blog post will discuss the two main views of the IBR. First, to be compliant with the Information Blocking Rule, healthcare providers and other entities must ensure they are not intentionally restricting or interfering with the access, exchange, or use of electronic health information. This includes implementing systems and processes that enable the seamless flow of patient data while adhering to appropriate security and privacy measures. Second, the Information Blocking Rule offers several benefits, including improved patient care through better access to their health information, reduced medical errors due to more complete and accurate data, and enhanced coordination among healthcare providers. This ultimately leads to better health outcomes for patients and a more efficient healthcare system.
Understanding Information Blocking Compliance
Specific actions by providers, health systems, payers, and hospitals may be considered information blocking. This includes refusing to provide access to electronic health information, imposing unreasonable fees, or using technology that restricts data sharing. By understanding the rule’s requirements and exceptions, entities can ensure they are complying with its provisions, and fostering a more interoperable healthcare ecosystem that benefits patients and providers alike.
The Impact of New Disincentives on Healthcare Providers
Disincentive regulations for healthcare providers went into effect on July 31, 2024. The new disincentive regulations for healthcare providers emphasize the importance of compliance with information blocking rules. These regulations, established by the U.S. Department of Health and Human Services (HHS), impose penalties on providers who: “engage in practices that the health care providers knew were unreasonable and were likely to interfere with, prevent, or materially discourage the access, exchange, or use of EHI, except as required by law or covered by a regulatory exception.”
Penalties for Non-Compliance
The penalties for non-compliance with IBR can be significant and vary depending on the severity of the violation. Here’s a breakdown:
Civil Monetary Penalties (CMP): The Office of Civil Rights (OCR) can impose civil monetary penalties of up to $1 million per violation.
Corrective Action Plan: OCR can require the non-compliant entity to develop and implement a corrective action plan to address the violation.
Public Disclosure: OCR can publicly disclose the name of the non-compliant entity and the nature of the violation.
Other Enforcement Actions: In addition to the above, OCR can also take other enforcement actions, such as issuing a Notice of Proposed Determination (NOPD) or a Notice of Enforcement Action (NOEA).
It’s important to note that the Information Blocking Rule also includes a “safe harbor” exception that protects entities from penalties if they can demonstrate that they are acting in good faith and have taken reasonable steps to comply with the rule. However, even with the safe harbor provision, it’s pivotal for entities to understand the rule’s requirements and to take steps to ensure compliance.
Source: Official Website of the Assistant Secretary for Technology Policy/Office of the National Coordinator for Health IT, HealthIT.gov
Benefits of HIEs to Support IBR Compliance
HIEs can facilitate compliance with the Information Blocking Rule. HIEs act as secure platforms for the exchange of electronic health information between different healthcare providers, enabling seamless data sharing and reducing the likelihood of information blocking. By providing a standardized infrastructure for data exchange, HIEs eliminate the need for providers to develop their own complex systems, which can help to reduce the risk of intentional or unintentional information blocking. Furthermore, HIEs promote interoperability by supporting data exchange in a standard and secure manner, making it easier for providers to access and share patient information. In this way, HIEs contribute significantly to a more interconnected healthcare ecosystem that assists with IBR compliance and benefits both patients and providers.
Conclusion
As healthcare continues to share data and information more frequently, the importance of adhering to information blocking regulations cannot be overstated. The penalties for non-compliance are significant, and the need for seamless access to patient data is critical. HIEs play an important role in helping healthcare providers and caregivers support the secure sharing and accessing of EHI.
UHIN operates and maintains the Clinical Health Information Exchange (The CHIE) that allows caregivers to improve access to data collected from outside of their system. The CHIE is the only HIE in Utah.
For many of us, Memorial Day marks the unofficial start to summer. Hard to believe we’re heading into June! In this month’s newsletter, we look at the importance of resilient, redundant and interoperable systems, the events and webinars coming up, and we attempt to foretell everything that will happen for the rest of the year.
The first half of this year was packed with exciting news and rocked by tech incidents. While we can’t predict the future, we can plan a better path ahead.
Look into your crystal ball 🔮 What are your predictions (big or small) for things to come in healthcare this year? And, what are your goals that you hope to accomplish? We want to hear from you!
Healthcare IT Today Podcast: Will the Change Healthcare Ransomware Attack Wake Up Healthcare?
John Lynn and Colin Hung look at where the industry stands just two months following the ransomware attack. For healthcare professionals, this could be a watershed moment for information security, revenue cycle management (RCM) and back-up planning for potential, future incidents.
Our most recent blog post (authored by Brian Chin, UHIN’s CEO) addresses the importance of redundant and resilient healthcare systems, and how they support seamless interoperability in times of crisis. There are, of course, great benefits and challenges when it comes to maintaining interoperability during disaster recovery (see them below👇).
September 13: Utah Medical Association (UMA) annual House of Delegates in Midvale, UT
October 15-17: Civitas Annual Conference in Detroit, MI
More to come: Stay tuned!
Trainings and Webinars
Upcoming Online Trainings & Webinars
We’ll host training sessions on the new CHIE platform, specifically for portal users. Stay tuned for more details on our virtual Payer Panels where you can ask questions and get answers from health plan representatives.
This month we announced our affiliation with Comagine Health and added new CHIE data sources from CommonSpirit Health. We look forward to growing with our new strategic partners, customers, and you! Keep reading for what else happened in April and what’s coming up next month.
P.S. Follow our LinkedIn page for more frequent news, posts and insights
Spotlight
UHIN and Comagine Health Announce Our Affiliation
“Aligning our health care knowledge and expertise through affiliation is a profound opportunity to advance our parallel missions, while delivering greater success to our customers and partners. We have collaborated successfully for more than a decade. As affiliates, UHIN and Comagine Health can serve as a unified force for change in health care for the foreseeable future.”
- Brian Chin, UHIN’s Chief Executive Officer
Keep scrolling for more information on our affiliation.
HIT News
The Full Release on our Affiliation
We have announced our official affiliation with Comagine Health, a national nonprofit healthcare consulting firm. We have a long history of working together over the last decade on federal and state initiatives to advance electronic health record (EHR) adoption, cost transparency reporting, capacity and functionality of all-payer claims databases (APCDs) and interoperability and surveillance activities. Combining our technology solutions and Comagine Health’s analytic services will enable more actionable health insights and more sustainable, transformational improvements for communities.
The CHIE adds CommonSpirit Health as a Data Source
The CHIE continues to add important data sources, providing healthcare professionals with vital medical information when it is needed most. Recently, we’ve onboarded CommonSpirit Health as a data source.
We’re attending the WEDI Spring Conference from May 13 – 16 (virtually). We look forward to learning more from experts, like Aneesh Chopra, about solutions to improve information exchange, enhance care quality, and reduce cost and burden.
In addition to online product trainings for our customers, we’re preparing virtual payer panels for later this year. These will be similar to the payer panels you may have attended in previous years at the HIT Conference.
Wrapping Up
Report: Significant Differences in Administrative Costs
We’re reading the recent CAQH report on the wide differences in administrative transaction costs for generalists, specialists and behavioral health providers. “The medical industry spends an astonishing $83 billion annually on staff time to conduct routine administrative transactions between providers and health plans during and after a patient-provider encounter. Providers shoulder 97 percent of these costs.”
The CHIE continues to add important data sources, providing healthcare professionals with vital medical information when it is needed most. Recently, we’ have’ve onboarded CommonSpirit Health as a data source.
These include:
Holy Cross Hospital – Davis (formerly known as Davis Hospital and Medical Center) in Layton
Holy Cross Hospital – Jordan Valley (formerly known as Jordan Valley Medical Center) in West Jordan
Holy Cross Hospital – Jordan Valley West (formerly known as Jordan Valley Medical Center-West Valley Campus) in West Valley City
Holy Cross Hospital – Mountain Point (formerly known as Mountain Point Medical Center) in Lehi
Holy Cross Hospital – Salt Lake (formerly known as Salt Lake Regional Medical Center) in Salt Lake City
And their clinics
CommonSpirit Health is a nonprofit, Catholic health system dedicated to advancing health for all people.